Pain rests at the crossroads of physiology, psychology, and social context. A paramedic supports a broken femur at 2 a.m., a registered nurse trainers a person via the very first 1 day after stomach surgical treatment, a physiotherapist rebuilds mobility while managing neuropathic discomfort flare‑ups. Each discipline sees a various face of the trouble, yet every one of them influence just how much the individual suffers and how quick they recuperate. That is why targeted pain monitoring training, from brief programs to formal accreditation, has come to be a core component of professional development for allied health.
This overview sets out what to anticipate from a pain administration program, just how qualification fits into practice for nurses, physio therapists, paramedics, and various other clinicians, and how specific frameworks like PUAEME008 Offer pain administration form day‑to‑day decisions in emergency situation settings. It leans on real scenarios, practical assessment pointers, and a frank check out trade‑offs you will certainly meet in the field.
The situation for structured discomfort education
Most medical professionals very first discover pain analysis in a generalist program. You remember the 0 to 10 numerical ranking scale, the Wong‑Baker encounters, and the fundamentals of NSAIDs versus opioids. After that fact makes complex things. A dementia patient that can't reveal demands. A teenager that looks fine yet rates their discomfort at 9. A post‑op situation where you titrate morphine only to find the pain is mainly spasm and fear. Without structured refreshers, practices embeded in and nuance fades.
Modern pain management training courses are made to shut that gap. Excellent programs bring a biopsychosocial lens, useful pharmacology, and skills for acute and chronic contexts. They additionally update you on safety and security criteria and legislation, as an example real‑time prescription surveillance, regional analgesic procedures, and non‑pharmacological adjuncts that meet standard limits for evidence.
What counts as a high quality discomfort management course
A reputable pain management certification course equilibriums theory and hands‑on method. Try to find evidence‑based educational programs, clear discovering end results, and evaluation that evaluates judgment as opposed to memorizing recall. When I evaluate a program for our group, I search for three fundamentals. First, organized assessment training that goes beyond a solitary range and includes function‑based procedures, red flag screening, and review intervals. Second, pharmacology that sets apart nociceptive, neuropathic, and combined discomfort, with clear dosing frameworks, titration methods, and security tracking. Third, non‑drug approaches that are more than platitudes: assisted pacing, graded exposure, breathing or leisure strategies, and device‑based alternatives like TENS with useful parameters.
Accreditation matters, yet the details vary by nation. Many pain monitoring training courses align to nationwide expertise frameworks or continuing professional advancement (CPD) criteria. In emergency situation contexts, discrete devices of competency like PUAEME008 Supply discomfort administration serve as benchmarks for paramedics, occasion paramedics, and very first -responders that require a firmly scoped ability for intense care.
Spotlight on PUAEME008 Provide discomfort management
PUAEME008 Give discomfort administration is a device of competency utilized in numerous Australian emergency treatment certifications. While the wording can vary in training plans, the significance corresponds: examine pain rapidly, choose ideal analgesia within extent and procedures, administer safely, screen feedback, and hand over precisely. I initially collaborated with a team transitioning from an older system to PUAEME008, and the modification forced cleaner documents habits and more regimented reassessment periods, which promptly enhanced client experience at sporting activities occasions and remote clinics.
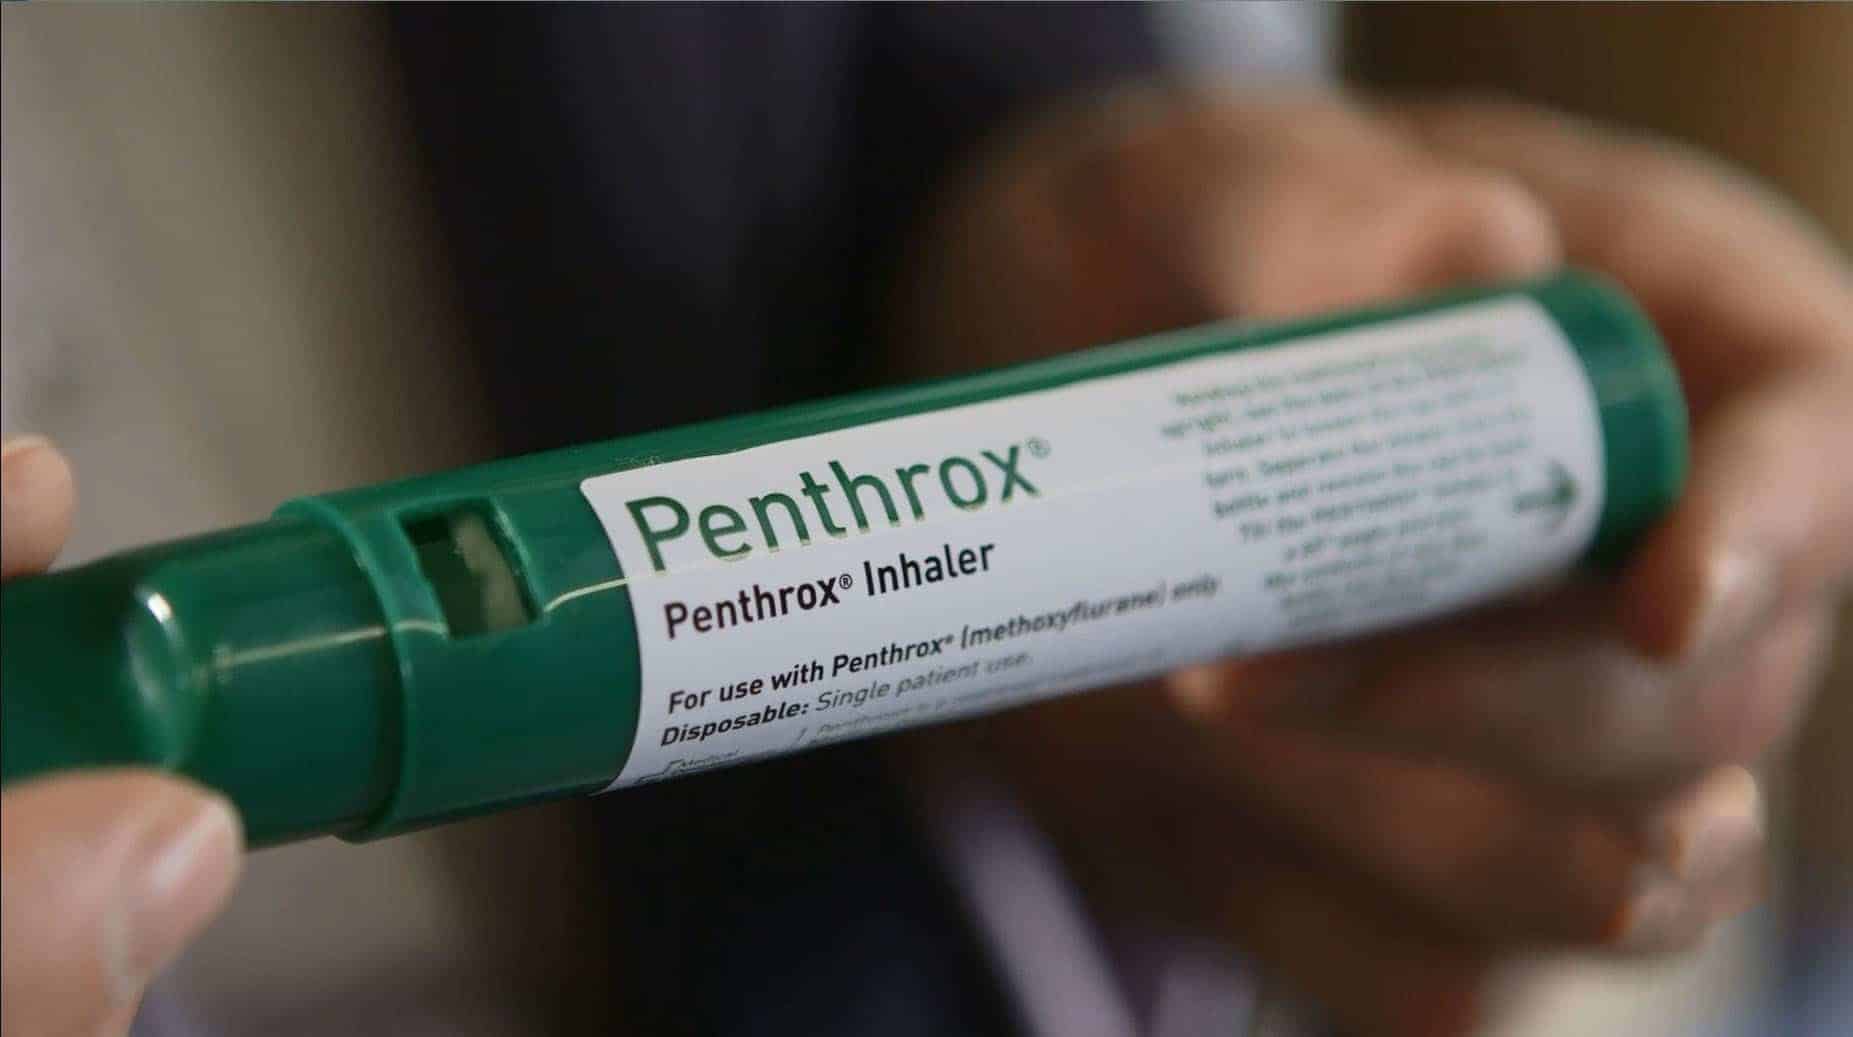
For medical professionals in these environments, the toughness of PUAEME008 is its functional clearness. You discover specifically when and how to release breathed in methoxyflurane for modest trauma pain, when to intensify to opioid analgesia within solution standards, just how to utilize complements like splinting and cool therapy, and just how to track sedation and respiration using standard observations. The unit likewise stresses verbal consent, contraindication testing, and rise to innovative care when pain is not reacting as expected.
If your duty includes emergency situation discomfort management in the area, a PUAEME008 provide discomfort monitoring program can be the distinction between improvisation and regimented practice. Companies often integrate it right into onboarding for event clinical staff, mine site medics, or remote location -responders, then audit records against unit standards during yearly skills checks.
Matching programs to professional roles
Not every discomfort management certification offers the exact same demand. A hospital nurse uses different levers than a community physio therapist, and a paramedic deals with unique time pressure and scene dangers. Pick training that respects your extent and context.
Nurses take advantage of pain monitoring courses for registered nurses that cover post‑operative paths, PCA device security, opioid stewardship, ecstasy risk, and communication with households that might merge sedation with comfort. Consist of components on non‑verbal discomfort evaluation for crucial care, and on useful topics like converting opioid doses during step‑downs from IV to dental regimens. Paediatric nursing requires unique focus to weight‑based dosing and developing communication.
Physiotherapists look for pain monitoring courses for physiotherapists that mix discomfort neuroscience education and learning, rated activity planning, and methods for central sensitization without appealing wonder remedies. A great program teaches you exactly how to rate progression when a client oscillates in between flare and worry evasion, how to integrate rest and stress and anxiety testing, and how to collaborate with prescribers when neuropathic attributes ask for medicine changes. Hand-operated treatment and exercise are still important, yet the frame changes from taking care of tissues to developing capacity.
Paramedics and very first responders need short programs in pain monitoring that emphasize fast evaluation, risk-free analgesic choice on the move, and practical adjuncts like immobilization and disturbance. Inhalational options, intranasal courses, and small‑volume gadgets matter when your person is entraped in an automobile or moving down a narrow stairwell. The PUAEME008 give discomfort management structure is extremely relevant here.
Allied health outside these classifications, such as occupational therapists, foot doctors, and radiographers, usually look for a certification course suffering monitoring to boost patient preparation and adherence. As an example, radiographers who trainer deep breathing and positioning can lower activity discomfort during imaging and boost study quality. OTs can educate energy conservation and task simplification that lower pain concern without medical changes.
Core content you must expect in a discomfort monitoring qualification course
Even as course titles differ, the core domains are surprisingly constant when programs are built on present evidence. Expect an organized development from device to management.
Assessment basics. You need to practice multiple scales, find out when to choose each, and support ratings to work. I encourage nurses to add 2 feature inquiries for any kind of confessed individual: what movement sets off discomfort most, and what does successful relief make it possible for in the following six hours. Reassessment protocols are just as important as initial racking up. A solid program requires paperwork of both peak pain and worst motion discomfort, considering that these are commonly different.
Pharmacology with guardrails. Pain administration training ought to differentiate nociceptive, neuropathic, and blended discussions, after that connect each to first‑line choices. For instance, neuropathic discomfort usually responds partially to gabapentinoids or SNRIs, while pure tissue injury might respond much better to NSAIDs and paracetamol, with opioids scheduled for brief windows. Titration techniques, maximum day-to-day doses, kidney and hepatic modifications, and medication interactions belong in the useful notes you really maintain the bedside or in your kit.
Non pharmacological methods with implementation information. Way too many programs checklist warmth, ice, and 10s without criteria. Quality training spells out timing, regularity, and hints for quiting. It also deals with cognitive methods like reframing discomfort signals throughout rated exposure, or exactly how to use breathing patterns during wound treatment. For persistent discomfort, you desire clear guidance on rest hygiene coaching, flare‑up planning, and micro‑goals that build a feeling of control.
Risk monitoring and opioid stewardship. Programs worth your time consist of material on opioid‑induced breathing clinical depression, irregularity prevention, and diversion threat. In 2020 our solution reduced ED monitoring time for modest trauma instances by about 15 percent after retraining team in a simple titration and reassessment cycle for IV morphine, paired with arranged laxatives and a handover manuscript. The auto mechanics are teachable, and they pay off.
Communication with patients and households. The very best discomfort management training for registered nurses and physiotherapists spends time on expectation setup. If you inform a patient that you are chasing comfort that permits coughing and strolling, not no pain, you straighten objectives and lower unnecessary acceleration. The mounting matters equally as much in a gym as in a ward.
Emergency pain management in the field
Acute pain in prehospital and occasion setups compresses time and raises variables. You could be functioning under rain, amid crowd sound, or in a confined bathroom. A concentrated discomfort administration course developed around emergency situation scenarios trains behaviors that endure chaos.
Scene security figures out whether you can do more than support. Splinting and positioning occasionally reduce pain more than medication in the first 5 mins, specifically for long bone fractures or shoulder dislocations. Breathed in analgesia like methoxyflurane can knock the pain down promptly while you prepare IV gain access to if procedures allow. Intranasal fentanyl has a role when venous gain access to is tough, however you require clear dosing tables and escalation requirements. PUAEME008 Supply discomfort management puts these choices right into a checklist structure that groups can debrief reliably after shifts.
Documentation is part of the therapy. I highlight a constant handover line to paramedics or ED personnel that includes system, top pain, feature support, interventions with times and doses, and the initial reassessment point. In method this avoids duplicate application and maintains the analgesic intend on a rational track.
Edge instances are entitled to focus. Elderly individuals with renal impairment and polypharmacy require traditional dosing and more constant observation. Individuals with opioid tolerance may need greater first dosages, yet they are equally as prone to unfavorable results if you stack sedatives. Agitated head injury complicates both analysis and analgesia selection. Quality discomfort management training courses attend to these without alarmism, providing practical choice trees.
Chronic discomfort, recovery, and the lengthy game
Chronic discomfort management is not the main target of every certificate course, yet also emergency‑focused programs need to give you a structure for the person who re-emerges repeatedly. A physiotherapist that comprehends central sensitization and anxiety avoidance can guide a cautious individual via rated activity with specific flare‑up policies. A nurse that clarifies that total pain silence is not the criteria can reset expectations that prevent unnecessary admission.
Behaviorally anchored strategies make the abstract sensible. For example, a person with chronic low pain in the back might commit to two walks per day, each just enough time to get to a 3 to 4 out of 10 boost suffering that solves to standard within 24-hour. This "expose yet do not bewilder" principle functions across joints and diagnoses, and it is teachable in a pain management accreditation training course with person scripts and examples.
Building a training prepare for your team
In busy solutions, education and learning competes with rosters and budgets. A blended method is typically the only feasible path. I have actually seen the very best results when organizations mix a fundamental discomfort management training course for all medical professionals with targeted components for details roles. For new beginners, a short certification training course in pain management that consists of PUAEME008 supply pain monitoring covers the intense base. For ward registered nurses, a ward‑based workshop on opioid conversions and PCA troubleshooting can reduce calls to after‑hours medical professionals. For physiotherapists, a two‑day pain neuroscience workshop paired with monitored case gets in touch with concretes skills.
One hospital I collaborated with cut post‑operative pain escalations by regarding a quarter over 2 quarters after implementing 3 modifications: a standard reassessment timetable installed in digital monitoring graphes, a simple nurse‑led path for oral multimodal analgesia within defined ceilings, and an interaction manuscript to set patient assumptions at admission. These changes grew workshops to provide pain management from training yet were sustained by workflow tweaks. Courses start the change, systems keep it going.
What evaluation and accreditation look like
Pain administration certification can be found in a number of tastes. Some are formal units like PUAEME008 with functional assessment and circumstance testing. Others are certificate programs used by universities or expert universities with online components, study, and proctored tests. The legitimate ones go beyond multiple option. Anticipate observed organized medical assessments, drug estimation checks, and substitute handovers. For registered nurses and paramedics, neighborhood drug authority recommendations or method sign‑offs could ride on the back of the course.

Keep an eye on recency demands. Abilities boring without use, specifically step-by-step analgesia and gadget usage. Good programs define re‑credentialing cycles, commonly every 2 to 3 years, and allow much shorter refresher components as opposed to repeating the whole discomfort administration qualification course.
Selecting a company without purchaser's remorse
Marketing language around discomfort management training is usually shiny. Strip it back with a couple of pragmatic checks.
- Faculty credibility: fitness instructors with existing clinical method, not simply scholastic titles. Ask how typically they operate at the bedside or in the field. Assessment roughness: a composed examination alone is not enough. Look for simulation, medication estimations, and observed functional skills. Protocol alignment: products must match your neighborhood medication formularies and lawful structures. Imported material without localization wastes time. Post program assistance: accessibility to updates, quick recommendation guides, and a line for concerns throughout the first months of implementation. Outcome monitoring: carriers who aid you measure modifications, such as reduction in time to very first analgesia or improved documents completeness.
These checks usually remove programs that guarantee a discomfort administration certification yet deliver little beyond slides.
Practical pharmacology, usual pitfalls, and more secure habits
Pain management training for nurses and paramedics often exposes patterns of over and under‑treatment. Under‑treatment originates from worry of opioids or missing non‑drug alternatives. Over‑treatment hides in piling sedatives or falling short to reassess after a first dose.
I instruct a routine loop that boosts safety. Dose decently within procedure, set a timer for reassessment, check pain, sedation, respiration, and function, after that determine whether to duplicate, change agents, or add a complement. The function anchor is essential. If a patient says pain is still 6, yet they can now cough, take a sip, and pivot sideways, that may be an appropriate plateau, especially in the very first hour after a severe injury or significant surgery.
Multimodal regimens function when they are really scheduled and complementary. Paracetamol on schedule, an NSAID if not contraindicated, a local option like topical diclofenac or lidocaine spots when appropriate, and regionals or blocks when offered. Opioids then cover optimals rather than develop the entire foundation. A great discomfort management program shows you how to compose these orders, discuss them with prescribers, and detect when a patient is getting on negative effects that must activate a switch.
Documentation that boosts treatment, not simply compliance
Documentation typically obtains mounted as a compliance job. Suffering monitoring it is a clinical device. The mix of a clear standard, an intervention document with times and dosages, and a practical target informs the following clinician where to get. I motivate brief yet specific access: "Discomfort 8 at rest, 10 on cough. Objective: cough and stay up with discomfort ≤ 6. Offered oxycodone 5 mg 14:05, paracetamol 1 g 14:10, showed cushion splinting. Reconsidered 14:35: pain 5 on cough, rested at edge of bed." That tight note aids the following registered nurse strategy and guards the individual from duplicate dosing.
Courses that include charting technique, particularly with neighborhood digital wellness records, deserve greater than refined theory alone. It is one point to understand you need to reassess in 20 to thirty minutes, and another to see specifically where to log it in your system so the alarm reminds you.
How physio therapists translate concept to movement
Physiotherapists usually appear of pain monitoring training stimulated however require anchors genuine sessions. Make use of one academic min at the start to frame the day's goal, then relocate into rated direct exposure with prompt wins. For instance, a client fearful of back flexion could begin with supported hip hinge drills to 20 levels, coupled with sluggish nasal breathing, after that advance to sit‑to‑stands with a padding. The workout selection issues less than the safety cues and development logic. Discomfort neuroscience education without an activity plan seldom sticks. A discomfort monitoring certificate course that pairs short, repeatable manuscripts with specific progressions is worth the time.
Nurses as organizers of the analgesic plan
On medical wards, registered nurses often coordinate the series of analgesia. A strong discomfort management training for nurses clarifies exactly how to time drugs about physiotherapy, injury treatment, and dishes. Providing a short‑acting opioid 20 minutes before chest physiotherapy can make the distinction in between productive coughing and superficial breathing. In a training programs to provide pain management similar way, think about night dosing to prevent 3 a.m. discomfort spikes that untangle rest and lengthen the recovery trajectory. When you see people as moving via a 24‑hour discomfort rhythm, not simply fixed vitals, your treatment timing improves.
Ethics, equity, and bias suffering assessment
Courses appropriately stress the auto mechanics of analgesia, but principles and equity matter just as much. Discomfort is under‑treated in certain populaces due to prejudice, communication barriers, or assumptions concerning drug‑seeking. Educating requirements to surface these patterns. Use interpreters early. For individuals with cognitive disability, lean on behavior ranges and family members understandings. Paper clearly when you decline or delay opioids and what option you offered. These routines protect people and clinicians, and they can be taught.

Making your qualification matter after the course
New abilities discolor if they live just in certifications. Fold what you discover right into everyday method. I ask groups to adopt one visible adjustment after a discomfort administration training course. Examples include standardizing a 30‑minute review window, including function‑based objectives to every analgesia strategy, or positioning a small "analgesia titration aid" card on the drug cart. Tiny artefacts keep the training active and spread it to brand-new colleagues.
Many clinicians collect numerous certificates over a job. Select deepness over quantity. A strong discomfort administration certification training course, refreshed with targeted updates every number of years, beats a loads shallow badges.
Where brief programs suit a lengthy career
Short training courses suffering administration fill the spaces in between huge career steps. A two‑hour update on intranasal analgesia, an early morning on neuropathic discomfort testing, an evening webinar on opioid conversions, each refines judgment and conserves time later. They also prepare you for bigger actions, such as an official discomfort administration certificate that may certify you to instruct peers or lead a service renovation project.
For paramedics and very first responders, a brief refresher anchored to PUAEME008 Give discomfort administration maintains skills sharp and documentation consistent across staffs. For ward nurses, bite‑sized sessions linked to neighborhood case assesses maintain the content grounded in reality.
Final thoughts from the floor
Pain monitoring is technical and human at once. The medicines, devices, and scales issue, yet the outcome hinges on what you observe, just how you time treatments, and just how you explain the strategy. The right pain management training course gives you the devices, however your method turns them right into alleviation the client can feel.
Choose programs that value your range, need actual evaluation, and show how to act under stress. If you operate in emergency situation treatment, a PUAEME008 supply discomfort management course is a sensible anchor. If you exercise on wards or in clinics, try to find pain monitoring qualification that links medication, motion, and attitude together. Then make the training visible in your notes, your discussions, and your regimens. That is how certifications come to be care.